
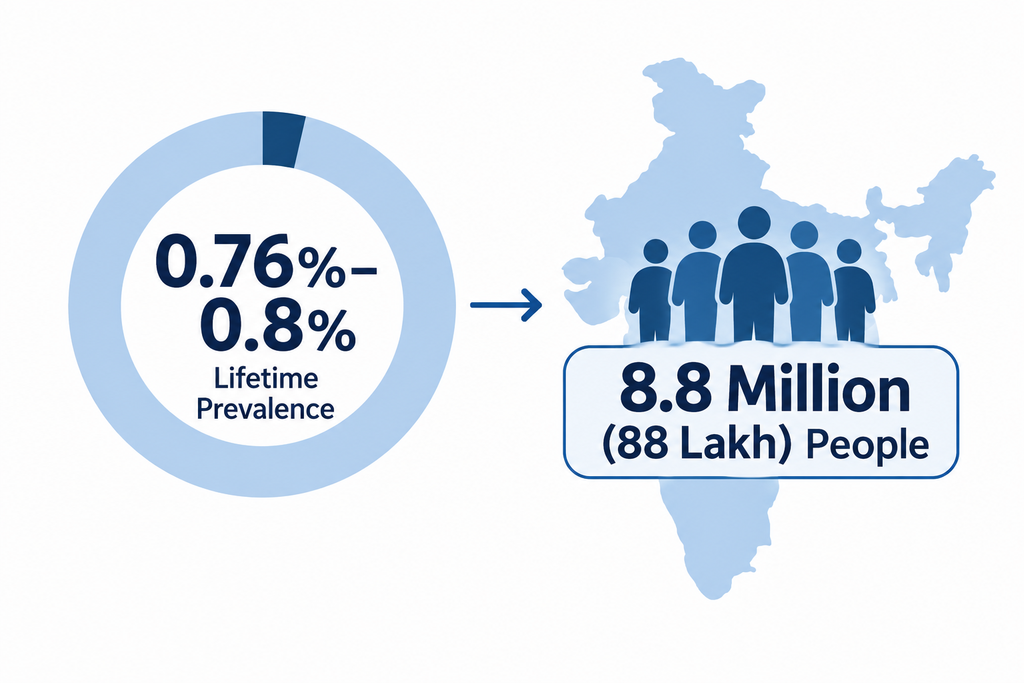
Obsessive compulsive disorder (OCD) is one of the most misunderstood conditions in modern psychiatry. In popular culture, OCD has become a casual word for being neat, precise or well organised. In clinical reality, it is a neurobiological disorder involving neural pathways and neurotransmitters. It creates a complex interplay between brain function, thought patterns and behaviour.
Understanding that difference matters. People with OCD often feel ashamed, hide their symptoms for years, and delay getting help because they assume their experience is just a quirk. OCD is treatable, and early help makes a real difference.
How OCD works: the obsession-compulsion cycle
OCD operates as a self-reinforcing loop with four phases.
- The obsession. These are persistent, unwanted and intrusive thoughts, images or urges. Unlike everyday worries, obsessions are highly distressing and completely out of step with the person’s values, wishes or character. Clinicians call this ego-dystonic.
- The distress. The intrusive thought triggers an immediate spike in anxiety, guilt or disgust, or a sense that something is fundamentally “not right”.
- The compulsion. To reduce this distress or prevent a feared outcome, the person repeats a behaviour or mental act. These can be visible, such as handwashing or checking locks, or entirely internal, such as mental reviewing, silent reassurance-seeking or counting.
- The temporary relief. The compulsion brings a brief drop in anxiety. But this relief reinforces the brain’s faulty alarm system and strengthens the belief that the compulsion was necessary to stay safe. That guarantees the loop will trigger again.
Types of OCD: harm, contamination, symmetry and more
Cleanliness and order are the best-known themes, but OCD shows up in many other ways. Recognising these is important for early diagnosis.
- Harm and aggression: Intrusive fears of harming yourself or someone else, even when you have no wish or intent to do so.
- Contamination: Fear of dirt, germs, toxins or “emotional contamination” from certain people or places.
- Symmetry and exactness: A strong urge to arrange objects in a specific, perfect order, or to repeat actions until they feel just right.
- Scrupulosity: Intense moral or religious obsessions about sin, blasphemy or ethical purity.
- Taboo thoughts: Highly distressing intrusive thoughts about sexuality or relationships, which cause intense self-doubt.
OCD treatment: medication and ERP therapy
Evidence-based treatment rests on two main pillars: medication and therapy.
Medication
- First-line: Selective serotonin reuptake inhibitors (SSRIs) are the main medicines used. Treating OCD usually needs higher doses of SSRIs than those used for depression.
- Augmentation: If symptoms do not improve, a psychiatrist may carefully add a low dose of an atypical antipsychotic. Clomipramine, a tricyclic antidepressant, is another option.
Exposure and response prevention (ERP) ERP is a specialised form of cognitive behavioural therapy (CBT) and is the benchmark psychological treatment for OCD. It has two parts:
- Exposure: The person deliberately faces the thoughts, objects or situations that trigger the obsessions.
- Response prevention: The person makes a planned choice to delay or resist the compulsion.
Over time, the brain learns that the feared outcome does not happen, or that the distress can be survived without the ritual. Therapists build a step-by-step exposure plan, starting with low-distress triggers and moving to harder ones.
Recognising compulsion substitution
A common setback in recovery is compulsions shifting from one form to another. Someone may stop washing their hands, then spend hours mentally reviewing events or constantly asking family for reassurance. Recovery means noticing these shifts and applying response prevention to all rituals, physical or mental.
Managing expectations in recovery
Recovery from OCD is rarely a straight line. Setbacks, flare-ups during stressful periods and brief returns of old loops are normal. Success is not the complete absence of intrusive thoughts. It is changing your relationship with them: learning to live with uncertainty without letting it control your behaviour.
How families can help: breaking the accommodation cycle
Family and close friends play an important role in recovery. Yet they often get caught in what is called family accommodation. Out of empathy and a wish to ease their loved one’s pain, they join in rituals. Examples include buying extra cleaning supplies, answering the same reassurance questions repeatedly or changing household routines.
Although well intended, research consistently shows that high levels of accommodation strengthen the OCD alarm system and are linked to poorer long-term outcomes.
Families can move from accommodation to support by setting kind, structured boundaries:
- Validate the emotion, not the fear. Acknowledge the distress without agreeing with the obsession. For example: “I can see you are feeling very anxious right now, and I know how hard this is.”
- Agree on a response in advance. Decide together how to decline reassurance requests. For example: “We agreed that answering this question feeds the OCD, so I am not going to answer it, because I want to support your recovery.
When to see a psychiatrist
Speak to a psychiatrist if intrusive thoughts or rituals take more than an hour a day, cause distress, or interfere with work, studies or relationships. Early treatment is much easier than treatment after years of symptoms.
If you are in crisis
If intrusive thoughts make you feel unsafe, or you have thoughts of harming yourself, contact someone immediately. In India, call Tele-MANAS on 14416 or 1-800-891-4416, a free government mental health helpline available 24 hours. For immediate danger, call 112 or go to the nearest emergency department.
Conclusion: working together for better outcomes
Better outcomes for people with OCD depend on a shared approach. When the public understands OCD as a serious neurobiological condition rather than a personality quirk, stigma falls and people seek help earlier. When clinicians use evidence-based treatments such as ERP consistently, recovery becomes far more likely. With clear information and support, OCD can move from a lifelong cycle of doubt to a condition that people manage well.
Book a consultation with AIMAN to talk through your symptoms with one of our psychiatrists or psychologists. Book online at aimanhealth.com/appointment or call +91 88008 33411.
Frequently asked questions
What causes OCD? OCD involves brain circuits and neurotransmitters, together with genetic and environmental factors. It is not caused by personality or poor parenting.
Is liking things neat the same as OCD? No. OCD involves intrusive thoughts that feel distressing and go against the person’s values, along with compulsions that bring only brief relief.
Can OCD be treated without medication? Yes. ERP therapy alone helps many people. Medication is an option when symptoms are severe or when the person prefers it. A psychiatrist can advise on the best approach.
About the author: Dr. Manya Agarwal
Dr. Manya Agarwal is a Consultant Psychiatrist at Aiman Health
She has completed her MBBS from AIIMS Jodhpur and MD Psychiatry from GMCH Chandigarh. She has also completed her Post doctoral fellowship in Acute care and emergency psychiatry from NIMHANS Bengaluru and has a wide range of clinical exposure in all and any kinds of Psychiatric illness and emergencies. Her areas of Interest being Schizophrenia and other Psychotic Disorders, Bipolar Affective disorders, Depressive disorders Obsessive compulsive disorders and Anxiety Neurosis.
Her approach is evidence based and patient centric catering to a holistic recovery.
Experience- 4+ years
